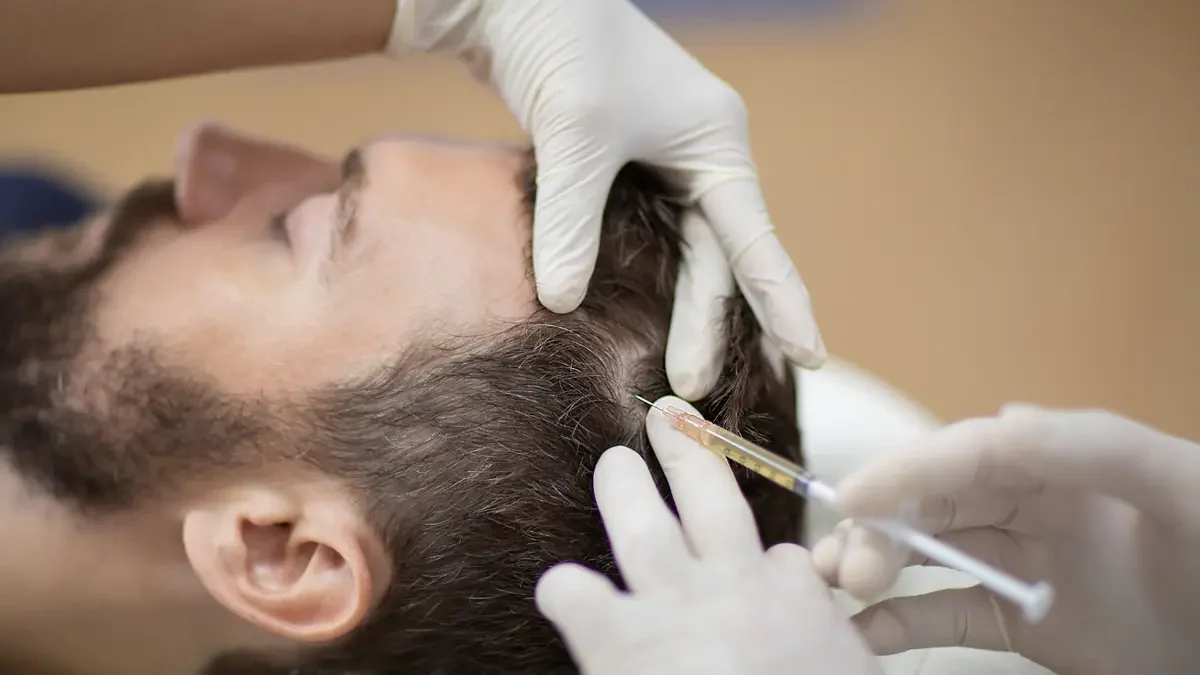
PRP for hair loss concentrates growth factors from your own blood and injects them into the scalp to support follicles that still exist; it does not create new ones. Trials show the most consistent benefit in early-to-moderate androgenetic alopecia, and a physician assessment with bloodwork decides suitability.
Platelet-rich plasma (PRP) for hair restoration occupies an interesting space — it has solid mechanistic logic, a meaningful but not miraculous evidence base, and is often oversold in marketing copy. This article walks through what PRP actually does at the follicle, what the controlled-trial literature supports, and how candidate evaluation should be structured.
For the program at Skin Art MD in Burnaby, BC, see the PRP hair restoration service page. To assess fit, book a consultation with our medical team.
How does PRP work on hair follicles?
PRP concentrates platelet growth factors and delivers them to the scalp, where lab and animal studies show they lengthen the growth phase, activate follicle cells and support blood supply to existing follicles.
Platelets are not just clotting agents. Their alpha granules contain a concentrated cocktail of growth factors and cytokines — PDGF, VEGF, IGF-1, EGF, TGF-beta — that participate in tissue repair and cell signalling. PRP preparation centrifuges autologous whole blood to concentrate these platelets several-fold above baseline, then injects the supernatant into the target tissue.
In the scalp, three follicle-relevant effects have been demonstrated in vitro and in animal models:
- Anagen phase extension. PRP-derived growth factors stimulate dermal papilla cells, the cluster of mesenchymal cells at the follicle base that controls hair cycle. Active dermal papilla = longer growth phase = thicker, longer hair shaft per cycle.
- Follicle progenitor-cell activation. Bulge region progenitor cells receive proliferative signals via PDGF and Wnt-pathway crosstalk. Dormant follicles can re-enter active growth.
- Microvasculature support. VEGF promotes localised angiogenesis. Better follicular blood supply correlates with healthier hair shaft production.
PRP does not create new follicles. The follicle inventory is fixed. PRP works by improving the function of follicles that still exist, including those that have miniaturised but not been lost.
What do clinical trials show about PRP for hair loss?
Randomised and review data show higher hair count and density with PRP, most consistently in early-to-moderate androgenetic alopecia, while results vary with how PRP is prepared.
The PRP-for-hair literature has matured over the last decade. Key studies:
- Gentile et al. (Stem Cells Translational Medicine). Randomised half-head trial in male androgenetic alopecia showed significantly higher hair count and density on the PRP-treated side at 6 months versus placebo.
- Cervelli et al. (BioMed Research International). Demonstrated similar hair count gains with three monthly sessions.
- Alves and Grimalt (Dermatologic Surgery). Reviewed 19 studies; concluded benefit is most consistent in early-to-moderate androgenetic alopecia and that protocol heterogeneity (single versus double-spin, activator versus no activator) likely contributes to mixed results across studies.
What the literature does not support: dramatic regrowth in advanced loss, success in scarring alopecia, or substitute status for medical workup of underlying conditions (thyroid disease, iron deficiency, autoimmune alopecia).
In Canada, PRP is prepared from the patient's own blood and performed as a medical procedure.
How does PRP compare with other hair loss treatments?
PRP supports existing follicles with growth factors, whereas minoxidil, oral prescription therapy and transplant surgery work through other mechanisms; PRP is often combined with medical therapy rather than used alone.
- Topical minoxidil prolongs anagen phase via vasodilation and direct follicle effects. Effective for many patients; daily commitment required.
- Oral prescription therapy lowers scalp DHT — the hormone driver in androgenetic alopecia. It requires a physician's evaluation of suitability and side effects.
- Hair transplant surgery redistributes existing follicles. The total follicle count does not change, but density in cosmetically important zones can be increased.
In practice, mechanisms are often combined: PRP plus minoxidil, or PRP alongside physician-prescribed oral therapy for genetically driven loss.
Who is PRP for hair loss commonly considered for?
PRP is mainly considered for early-to-moderate pattern hair loss and some diffuse thinning, and is less suited to advanced or scarring hair loss; a physician consultation with bloodwork decides suitability.
Situations commonly assessed:
- Early-to-moderate androgenetic alopecia (Norwood I-IV / Ludwig I-II).
- Telogen effluvium that has not resolved with treatment of the underlying cause.
- Diffuse thinning without distinct patterning.
PRP works less well or is inappropriate for:
- Advanced loss (Norwood VI-VII): too few viable follicles remain to respond.
- Scarring alopecias (lichen planopilaris, frontal fibrosing alopecia, central centrifugal cicatricial alopecia): require medical (often immunosuppressive) management; PRP alone is insufficient.
- Active scalp inflammation or infection.
- Bleeding disorders, anticoagulation, or platelet dysfunction.
A proper consultation includes:
- Family history and pattern assessment.
- Bloodwork (CBC, ferritin, vitamin D, thyroid, hormones if indicated).
- Trichoscopy where available.
- Discussion of expectations and integration with medical therapies.
At Skin Art MD, this evaluation is led by Dr. Sharon Fong.
What are the limits of PRP for hair loss?
Results from PRP hair treatment take 3-6 months to become visible, require maintenance sessions, and vary between patients.
- Visible change takes 3-6 months. The hair cycle is slow.
- Maintenance is required. Most clinical responders need a session every 4-6 months after the initial 3-4 session loading phase to sustain results.
- Response varies. Some patients see meaningful density gains; others see stabilisation without dramatic regrowth. A clinic that promises uniform dramatic results is overstating.
- PRP is usually part of a broader plan. A reasonable program includes minoxidil and, where appropriate, oral medical therapy.
What do people ask about PRP for hair loss?
Common questions cover the number of sessions, comfort, when results appear, combining PRP with minoxidil, and use in women.
How many sessions will I need? Standard induction is 3-4 sessions at 4-6 week intervals. Maintenance is typically every 4-6 months thereafter. Individual response determines actual schedule.
Does it hurt? The scalp is anaesthetised before injection. Most patients describe pressure rather than pain. Mild post-procedure tenderness is common and usually resolves within 24 hours.
When will I see results? Visible change typically emerges between months 3 and 6. Photo documentation at baseline and 6 months is a reliable comparator.
Can I combine PRP with minoxidil? Yes. Minoxidil and PRP have complementary mechanisms and are often combined for androgenetic alopecia.
Is PRP used for women? Yes, particularly for diffuse thinning patterns; a physician assessment decides suitability. Hormonal evaluation (thyroid, iron, androgens) precedes PRP for female patients.
Why choose Skin Art MD for PRP?
Skin Art MD in Burnaby, BC provides physician-supervised PRP under the care of Dr. Sharon Fong. Protocols are individualised after baseline workup, and we structure programs to combine PRP with appropriate medical therapy rather than offering it as a stand-alone service. Bilingual care available in English and Mandarin.
Next Steps
The useful next step is a focused consultation with bloodwork and a candid conversation about pattern, severity, and realistic outcomes. Book your consultation today.
This article is for educational purposes only and does not constitute medical advice. Please consult with a qualified healthcare professional before undergoing any treatment.